If your child or a family member has been diagnosed with a Ventricular Septal Defect (VSD) and you are trying to make sense of the echo report, you are not alone. One of the first questions most families ask is, “What size of Ventricular Septal Defect (VSD) requires surgery?”
The honest answer is that the size of the defect matters, but it is only a part of the picture.
This guide walks you through what the echo findings actually mean and when VSD closure surgery becomes necessary.
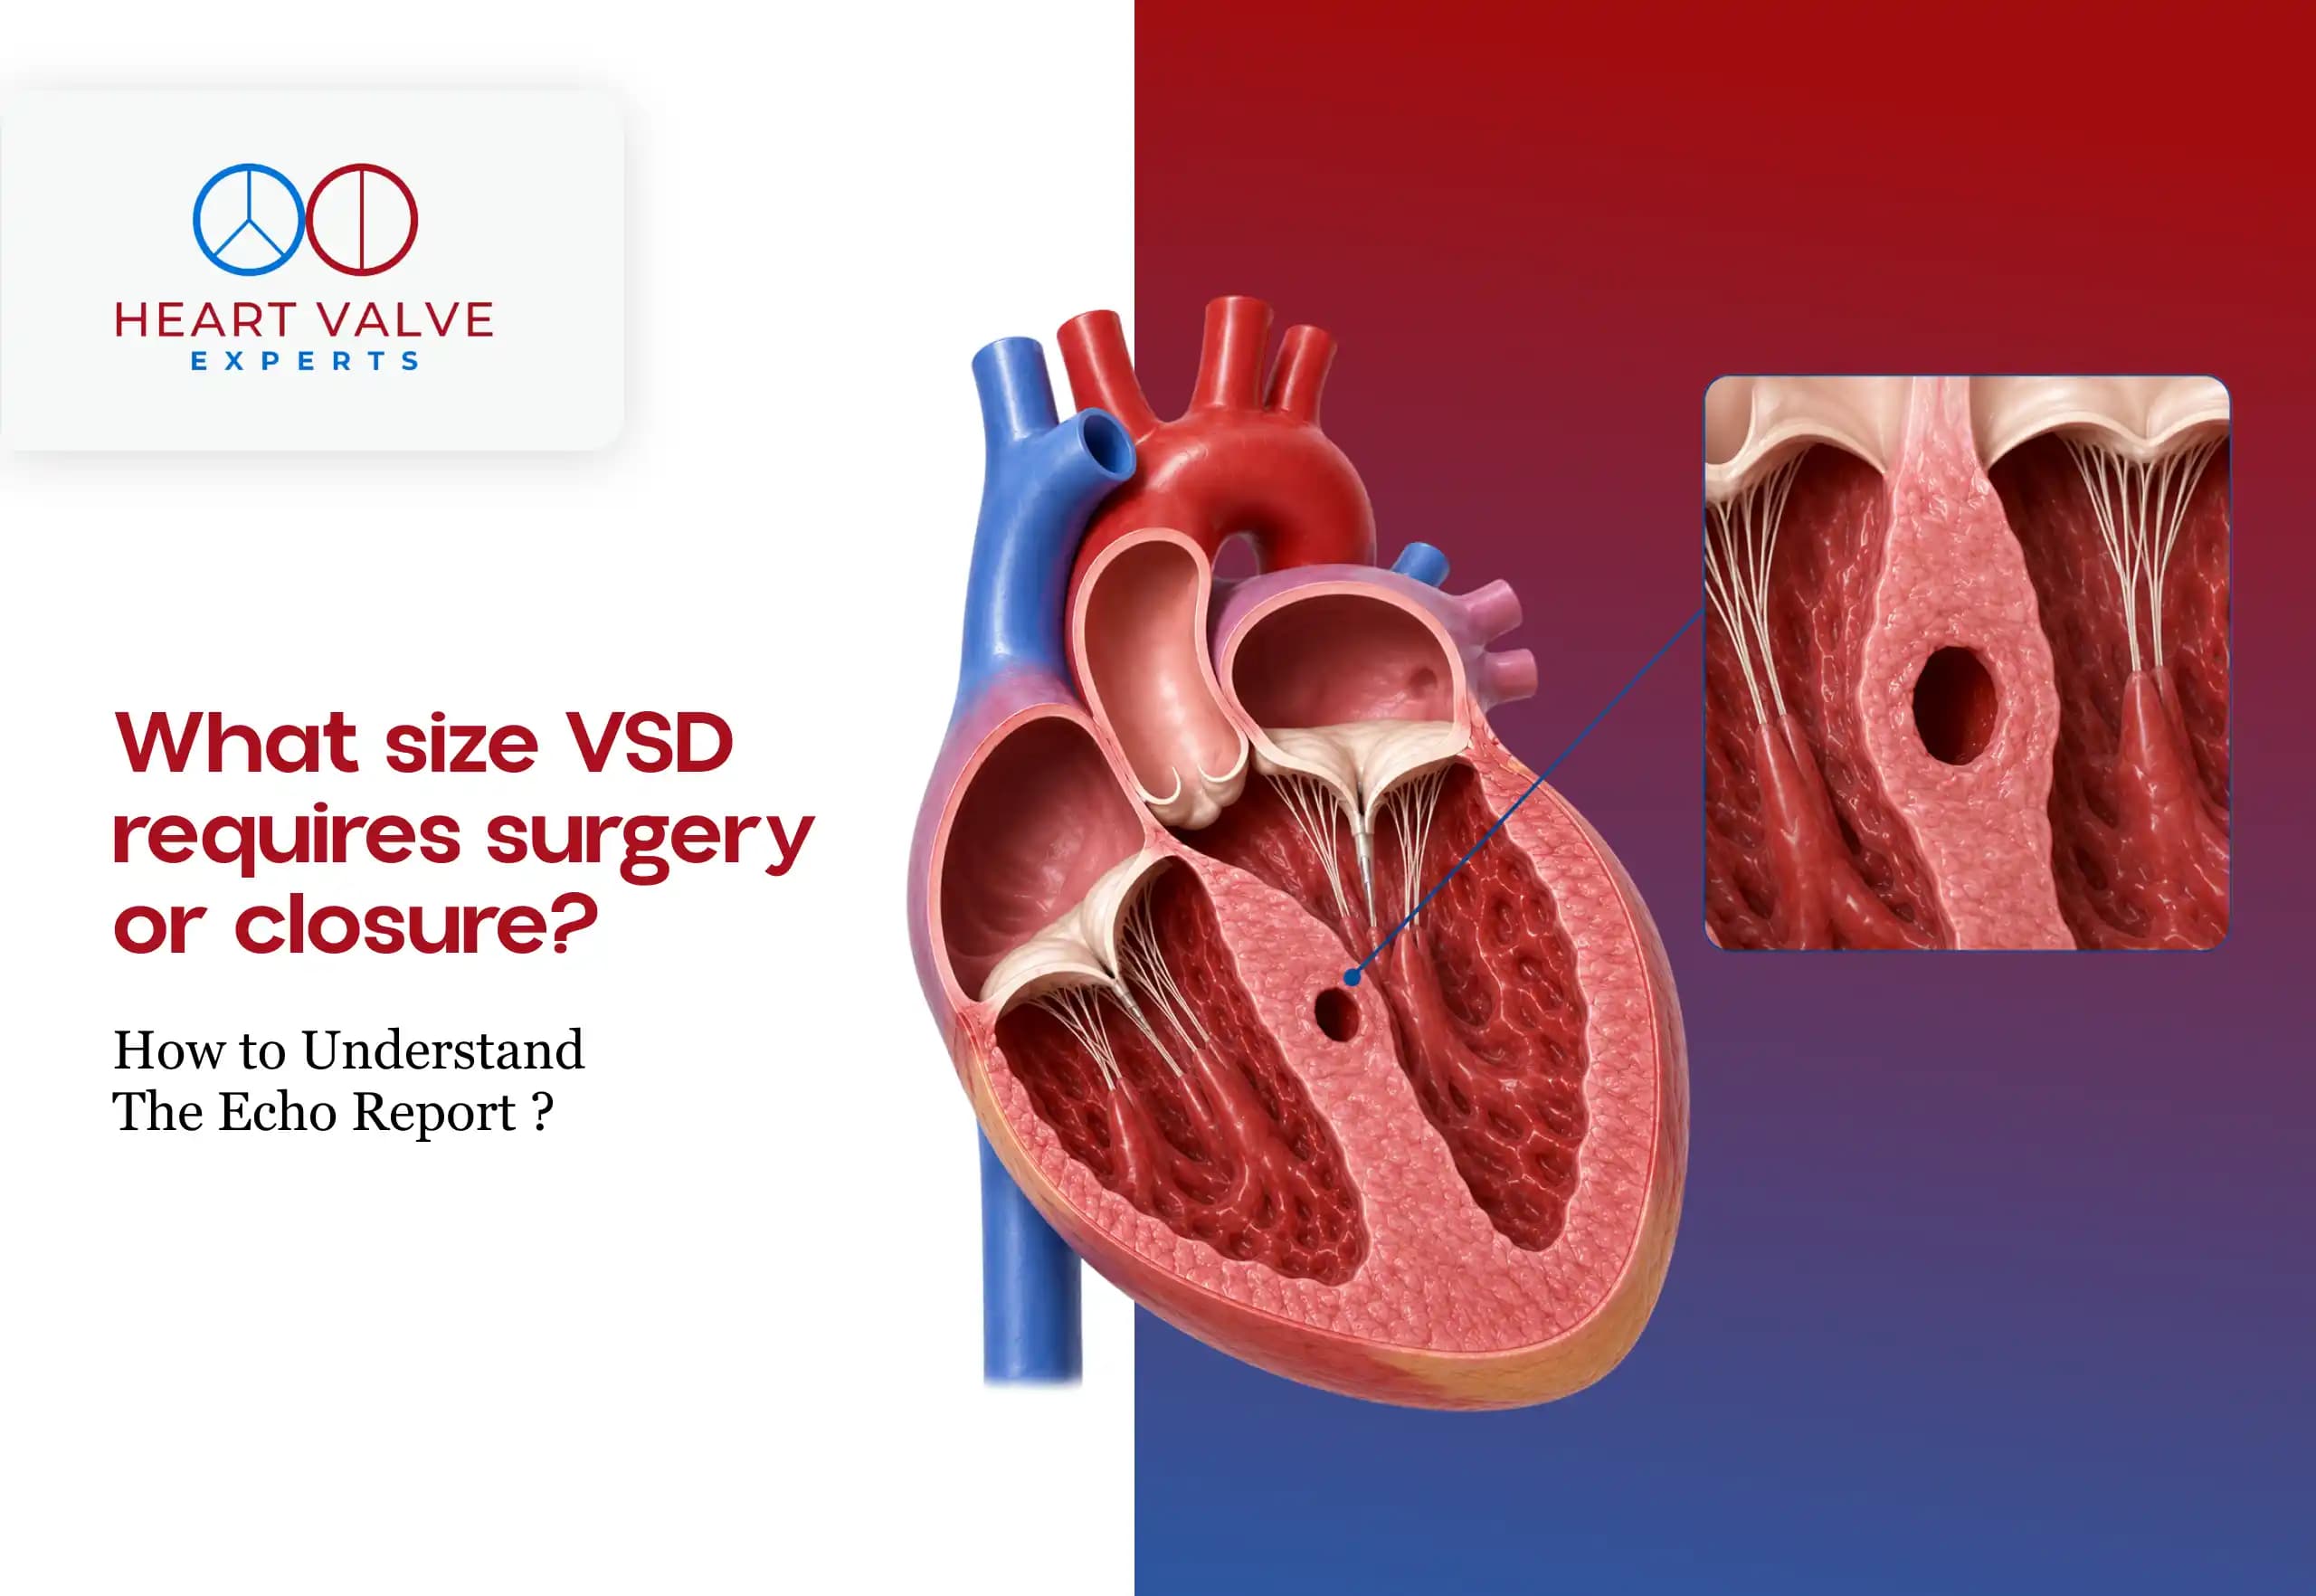
A ventricular septal defect is a hole in the wall (septum) that separates the two lower chambers of the heart. The oxygenated blood from the left ventricle leaks back into the right ventricle, making the heart work harder than it should. VSD is the most common congenital heart defect found in children and also appears in adults.
Not all ventricular septal defects are the same. They vary in size, location, and how much they affect heart function. All three factors together determine whether the defect needs to be closed or can simply be monitored.
When a cardiologist orders an echocardiogram, one of the key measurements reported is the size of the VSD in millimetres.
Here is how sizes are generally interpreted:
These are general ranges. The exact thresholds can vary depending on the patient’s body size, age, and overall cardiac anatomy.
| VSD Size | Shunting | Symptoms | Action Typically Needed |
| Small (less than 3 to 5 mm) | Minimal | Usually none | Monitor; may close on its own |
| Moderate (5 to 10 mm) | Moderate | Mild to moderate | Monitor closely; closure if needed |
| Large (greater than 10 mm) | Significant | Heart failure, poor growth | Closure usually recommended |
Here is the clinical reality:
The key takeaway: size alone does not determine the need for VSD surgery. The echo findings need to be interpreted alongside symptoms, heart chamber sizes, pulmonary artery pressure, and the ratio of pulmonary to systemic blood flow.
In children, the approach is primarily driven by growth, symptoms, and the risk of developing pulmonary hypertension. Infants with large VSDs who are not growing are prioritised for early VSD closure surgery. Older children with moderate defects and left ventricular dilation are also strong candidates.
In adults, VSDs are less commonly encountered, but when they are, the evaluation is different. Adults with small, restrictive VSDs and normal pulmonary pressure and no symptoms may be monitored without intervention. However, adults with a history of untreated moderate to large VSDs may present with pulmonary hypertension, arrhythmias, or reduced exercise capacity, all of which change the management approach significantly.
In both age groups, an echocardiogram remains the primary tool for decision-making.
Seek a cardiology opinion promptly if the child or adult with a known VSD shows any of the following:
If your cardiologist recommends closure, the next step is determining which approach is best suited for the specific defect:
The choice between the two depends on the defect’s size, location, proximity to valves, and the patient’s overall health.
Post-closure, most patients recover well. Infants typically stay in the hospital for five to seven days after open surgery, while catheter-based closure allows discharge in two to three days. Long-term outcomes are excellent when closure is done at the right time.
Understanding a Ventricular Septal Defect (VSD) diagnosis and deciding the right course of action requires more than just reading an echo report. Heart Valve Experts connects patients and families with experienced congenital and structural heart specialists who can evaluate your specific case, explain what the findings mean, and guide you on whether monitoring or VSD closure surgery is the right step. If you have questions or need a second opinion, reach out to the Heart Valve Experts team for a consultation.


About The Author
With over 15 years of expertise, Dr. Phatarpekar is recognised as a renowned interventional cardiologist in Mumbai, specialising in complex coronary interventions, structural heart procedures, and pioneering work in Transcatheter Aortic Valve Implantation (TAVI).
● Blogs