If you have been told that you may need heart valve surgery, it is normal to have questions. Do you need treatment now? Can the valve be repaired instead of replaced? Is a less invasive procedure possible? How should you compare hospitals offering heart valve disease treatment in Mumbai?
Heart valve treatment is not simply about finding a hospital that performs an operation. The first step is confirming what is wrong with the valve, how severe it is and which treatment is appropriate for you. For significant valve disease, decisions may involve a multidisciplinary Heart Team, which can include cardiologists, cardiac surgeons, interventional cardiologists, imaging specialists and anaesthesiologists.
The following questions can help you make a more informed decision.
First, Understand Your Heart Valve Disease and Treatment Options
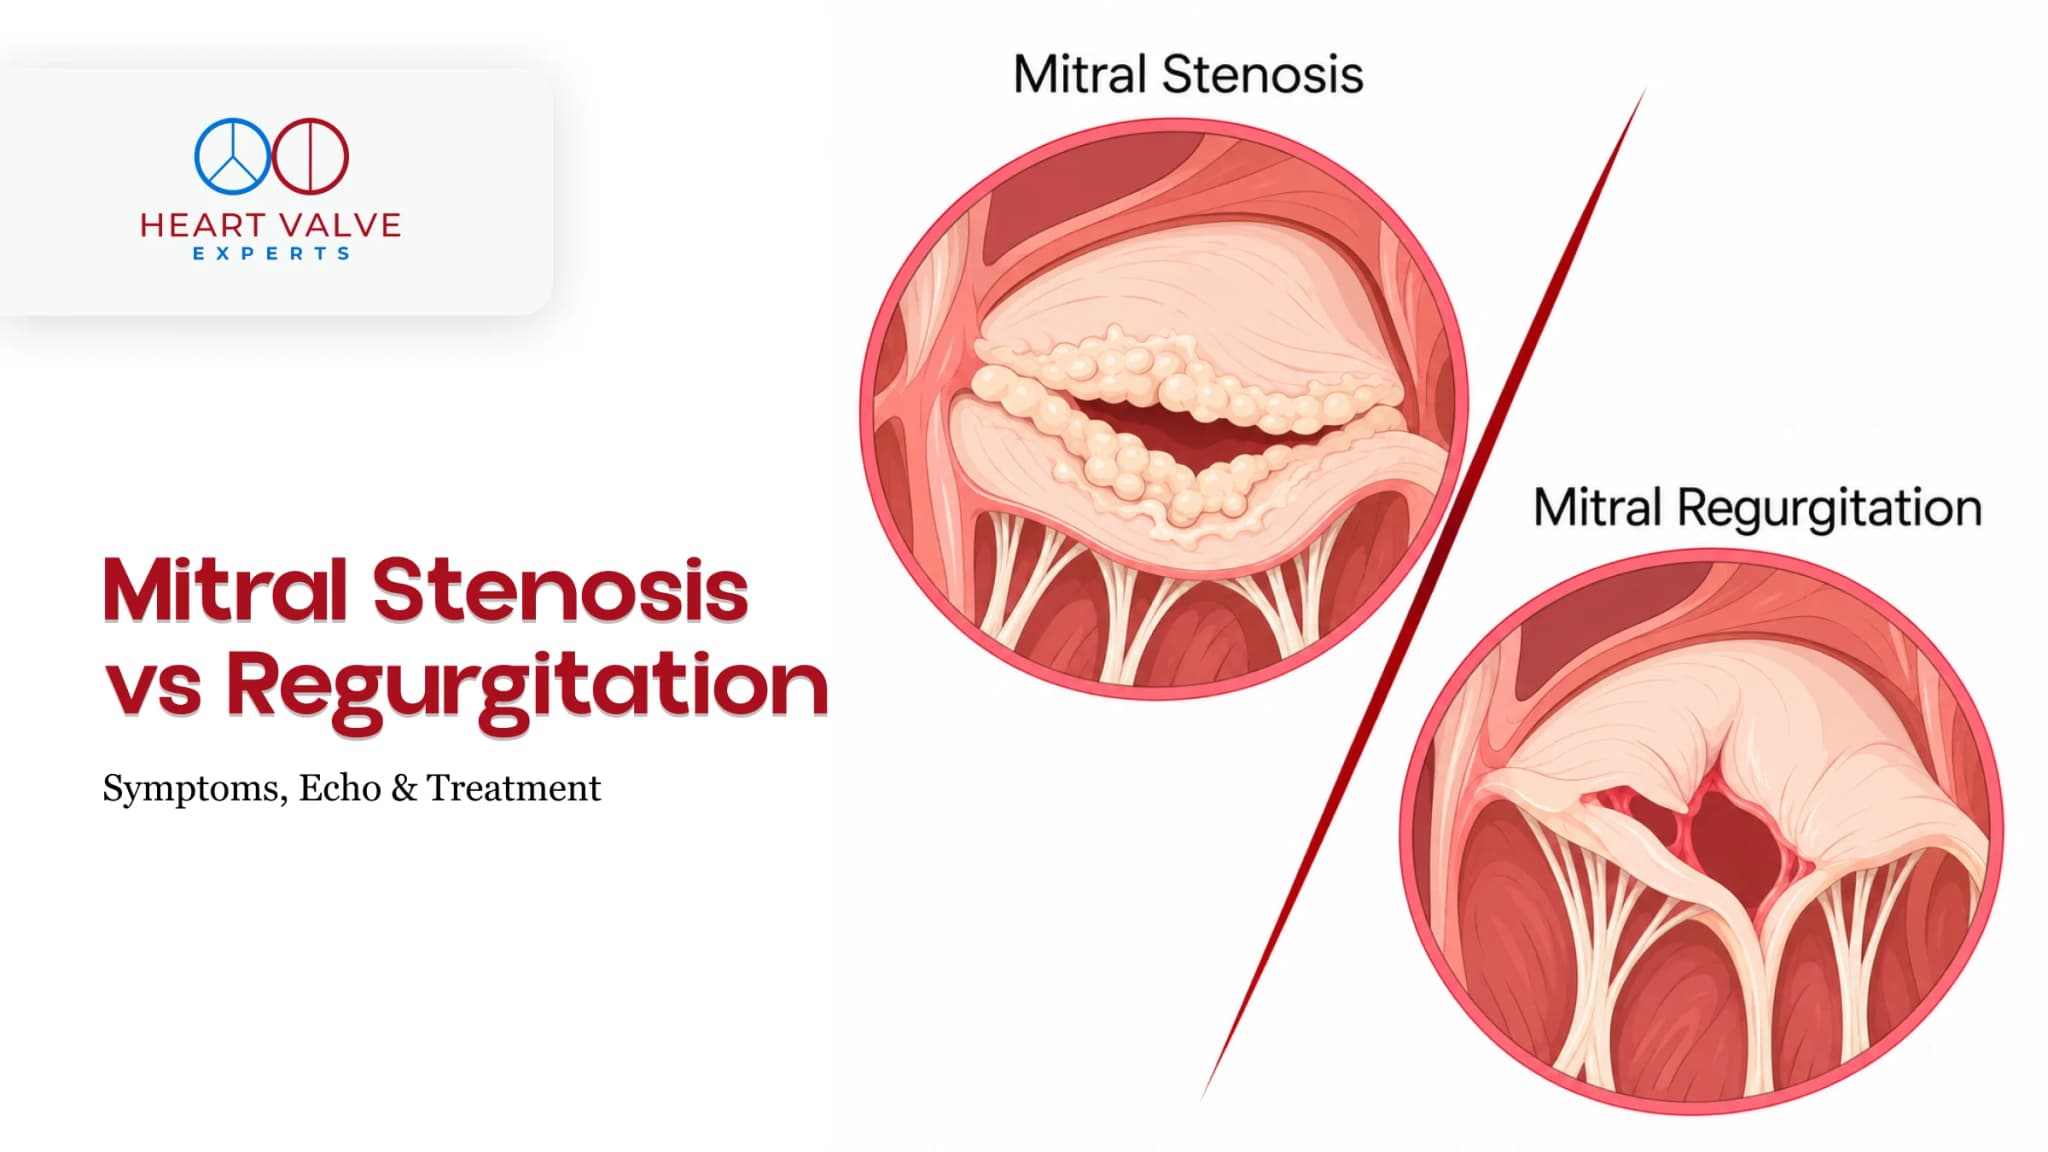
The heart has four valves: aortic, mitral, tricuspid and pulmonary. A valve may become too narrow, called stenosis, or may not close properly, causing backward leakage, called regurgitation. Heart valve disease treatment in Mumbai typically starts with confirming exactly which valve is affected and how severe the problem is before any procedure is discussed.
Not everyone with heart valve disease needs immediate intervention. The decision depends on the affected valve, the cause and severity of the problem, symptoms, changes in heart function, age, general health and the likely benefits and risks of treatment. Options may include monitoring, valve repair, valve replacement, minimally invasive surgery or a catheter-based procedure such as TAVI.
Heart valve care can involve several decisions: whether treatment is needed, when it should happen and whether repair, replacement, conventional surgery or a catheter-based procedure is most suitable.
Ask whether the relevant specialists will review your medical history and actual scan images before recommending treatment. You should receive clear answers to questions such as:
The recommendation should reflect your valve anatomy, symptoms, overall health, expected benefit and personal preferences, not simply the procedures available at one hospital.
“Heart valve surgery” includes many different procedures. Treating aortic stenosis differs from managing mitral regurgitation, disease affecting several valves or a problem in someone who has previously undergone heart surgery.
Instead of asking only how many heart operations the hospital performs, ask how frequently the team treats patients with your specific condition and proposed procedure. If you have mitral regurgitation, for example, ask whether repair has been considered. A durable repair may be preferred for appropriately selected patients, but replacement may be more suitable in other cases.
Before any treatment is planned, your medical team needs a clear understanding of what is happening with your heart valve and how it is affecting your heart.
An echocardiogram, which uses ultrasound to create images of the heart, is usually one of the first and most important tests. Depending on your valve condition and the treatment being considered, you may also need a more detailed echocardiogram, CT scan, cardiac MRI, assessment of the coronary arteries or other tests.
You do not need to interpret every scan or understand every medical term. However, before making a treatment decision, you should feel confident that you understand:
If something is unclear, ask your doctor to explain it differently or show you the relevant findings on your scan. You should feel comfortable asking questions. An accurate diagnosis and a clear explanation can help you take part in the treatment decision with greater confidence.
Being told that you may need a heart valve procedure can make it seem as though open-heart surgery is the only option. However, not everyone with valve disease needs surgery, and even when treatment is necessary, the least invasive option is not automatically the safest or most suitable choice.
Depending on which valve is affected, your valve anatomy and your overall health, suitable options may include surgical repair, surgical replacement, minimally invasive heart valve surgery, TAVI or another transcatheter procedure.
Ask your Heart Team to explain which options are genuinely suitable for you, along with the benefits, possible risks, expected recovery and how long the results may last. The goal is not to choose the treatment that sounds newest or most advanced, but the one that offers the most appropriate balance of safety, effectiveness and long-term benefit for your individual condition.
Procedure volume can indicate experience, but high volume alone does not prove quality. Ask whether the hospital tracks outcomes such as survival, stroke, bleeding, kidney problems, infection, readmission, repeat procedures and valve function after treatment.
If you are given a “success rate,” ask what it measures and whether it applies to patients with a condition and risk profile similar to yours. Individual risk can be influenced by age, heart function, kidney or lung disease, previous surgery, frailty and procedural complexity.
The hospital should also have appropriate cardiac imaging, anaesthesia, intensive care and clinical teams to recognise and manage potential complications.
Before providing consent, ask which valve will be treated, whether it will be repaired or replaced, what will happen if repair is not possible and whether another heart problem will be treated during the same operation.
If replacement is recommended, discuss the choice between a mechanical valve and a biological or tissue valve. Mechanical valves are durable, but patients generally require lifelong anticoagulation with a vitamin K antagonist such as warfarin and regular INR monitoring. Tissue valves do not usually require lifelong warfarin solely because of the valve, but they may deteriorate over time.
Age, bleeding risk, lifestyle, pregnancy plans where relevant, ability to take anticoagulants and the possibility of future procedures may influence the choice.
Ask about the expected hospital stay, pain management, walking and physiotherapy, wound care, medicines, cardiac rehabilitation, repeat scans and return to normal activities. Find out who to contact if you become unwell after discharge.
Recovery varies between patients and procedures. Ask what your likely recovery pathway will involve rather than relying on another person’s experience.
Ask for a written estimate explaining what is included. Costs may involve the procedure, valve or repair materials, intensive care, hospital stay, professional fees, tests, medicines and follow-up.
Clarify what could increase the final bill, whether insurance pre-authorisation is required, whether government schemes are accepted and whether follow-up is included. A detailed valve-replacement cost guide may help you understand possible cost components, but your hospital must provide an individual estimate.
Cost matters, but the lowest estimate should not be the only deciding factor. Clinical suitability, team experience, hospital support and follow-up are equally important.
A second opinion does not mean that the first doctor is wrong. Another specialist may confirm the same recommendation, offer an alternative or explain the decision more clearly.
Consider another opinion if:
For a useful Heart Team second opinion, share the actual scan images and reports, ECGs, blood-test results, medication list, previous discharge or operation records and the proposed treatment plan.
Do not wait for a routine second opinion if you are acutely unwell. Seek emergency medical care for severe or sudden breathlessness, chest pain with sweating or faintness, fainting with known severe valve disease, possible stroke symptoms or rapidly worsening symptoms of heart failure.
The right hospital is not necessarily the one with the biggest name, newest advertised technology or lowest price. Look for a team that can accurately assess your condition, discuss all reasonable options, explain individual benefits and risks and provide coordinated care before, during and after treatment.
If valve repair or replacement has been recommended and you still have questions, a Heart Team review can help you understand whether the proposed timing and treatment approach are appropriate for your condition.
No hospital is right for every patient. Consider the team’s experience with your condition, multidisciplinary assessment, imaging and critical-care facilities, outcome monitoring, treatment options and follow-up support.
No. It may offer advantages for selected patients, but suitability depends on the affected valve, anatomy, general health, other required procedures and the team’s expertise.
Sometimes. A durable repair may be preferred for certain valve problems, particularly some forms of mitral regurgitation. Replacement may be more appropriate in other situations. Ask why one approach is recommended for you.
Yes, if your condition is stable and a brief delay is considered safe. Obtain your scan images, reports and proposed treatment plan. Do not delay urgent treatment if you are acutely unwell.
Neither is best for everyone. The choice depends on durability needs, age, bleeding risk, anticoagulation, lifestyle, pregnancy considerations and possible future procedures.

About The Author
With over 15 years of expertise, Dr. Phatarpekar is recognised as a renowned interventional cardiologist in Mumbai, specialising in complex coronary interventions, structural heart procedures, and pioneering work in Transcatheter Aortic Valve Implantation (TAVI).
● Blogs