An atrial septal defect (ASD) is an opening between the two upper chambers of the heart that is present from birth. Some ASDs cause no obvious symptoms for many years and may only be detected in adulthood during a heart scan or after symptoms such as breathlessness, reduced exercise capacity or palpitations develop.
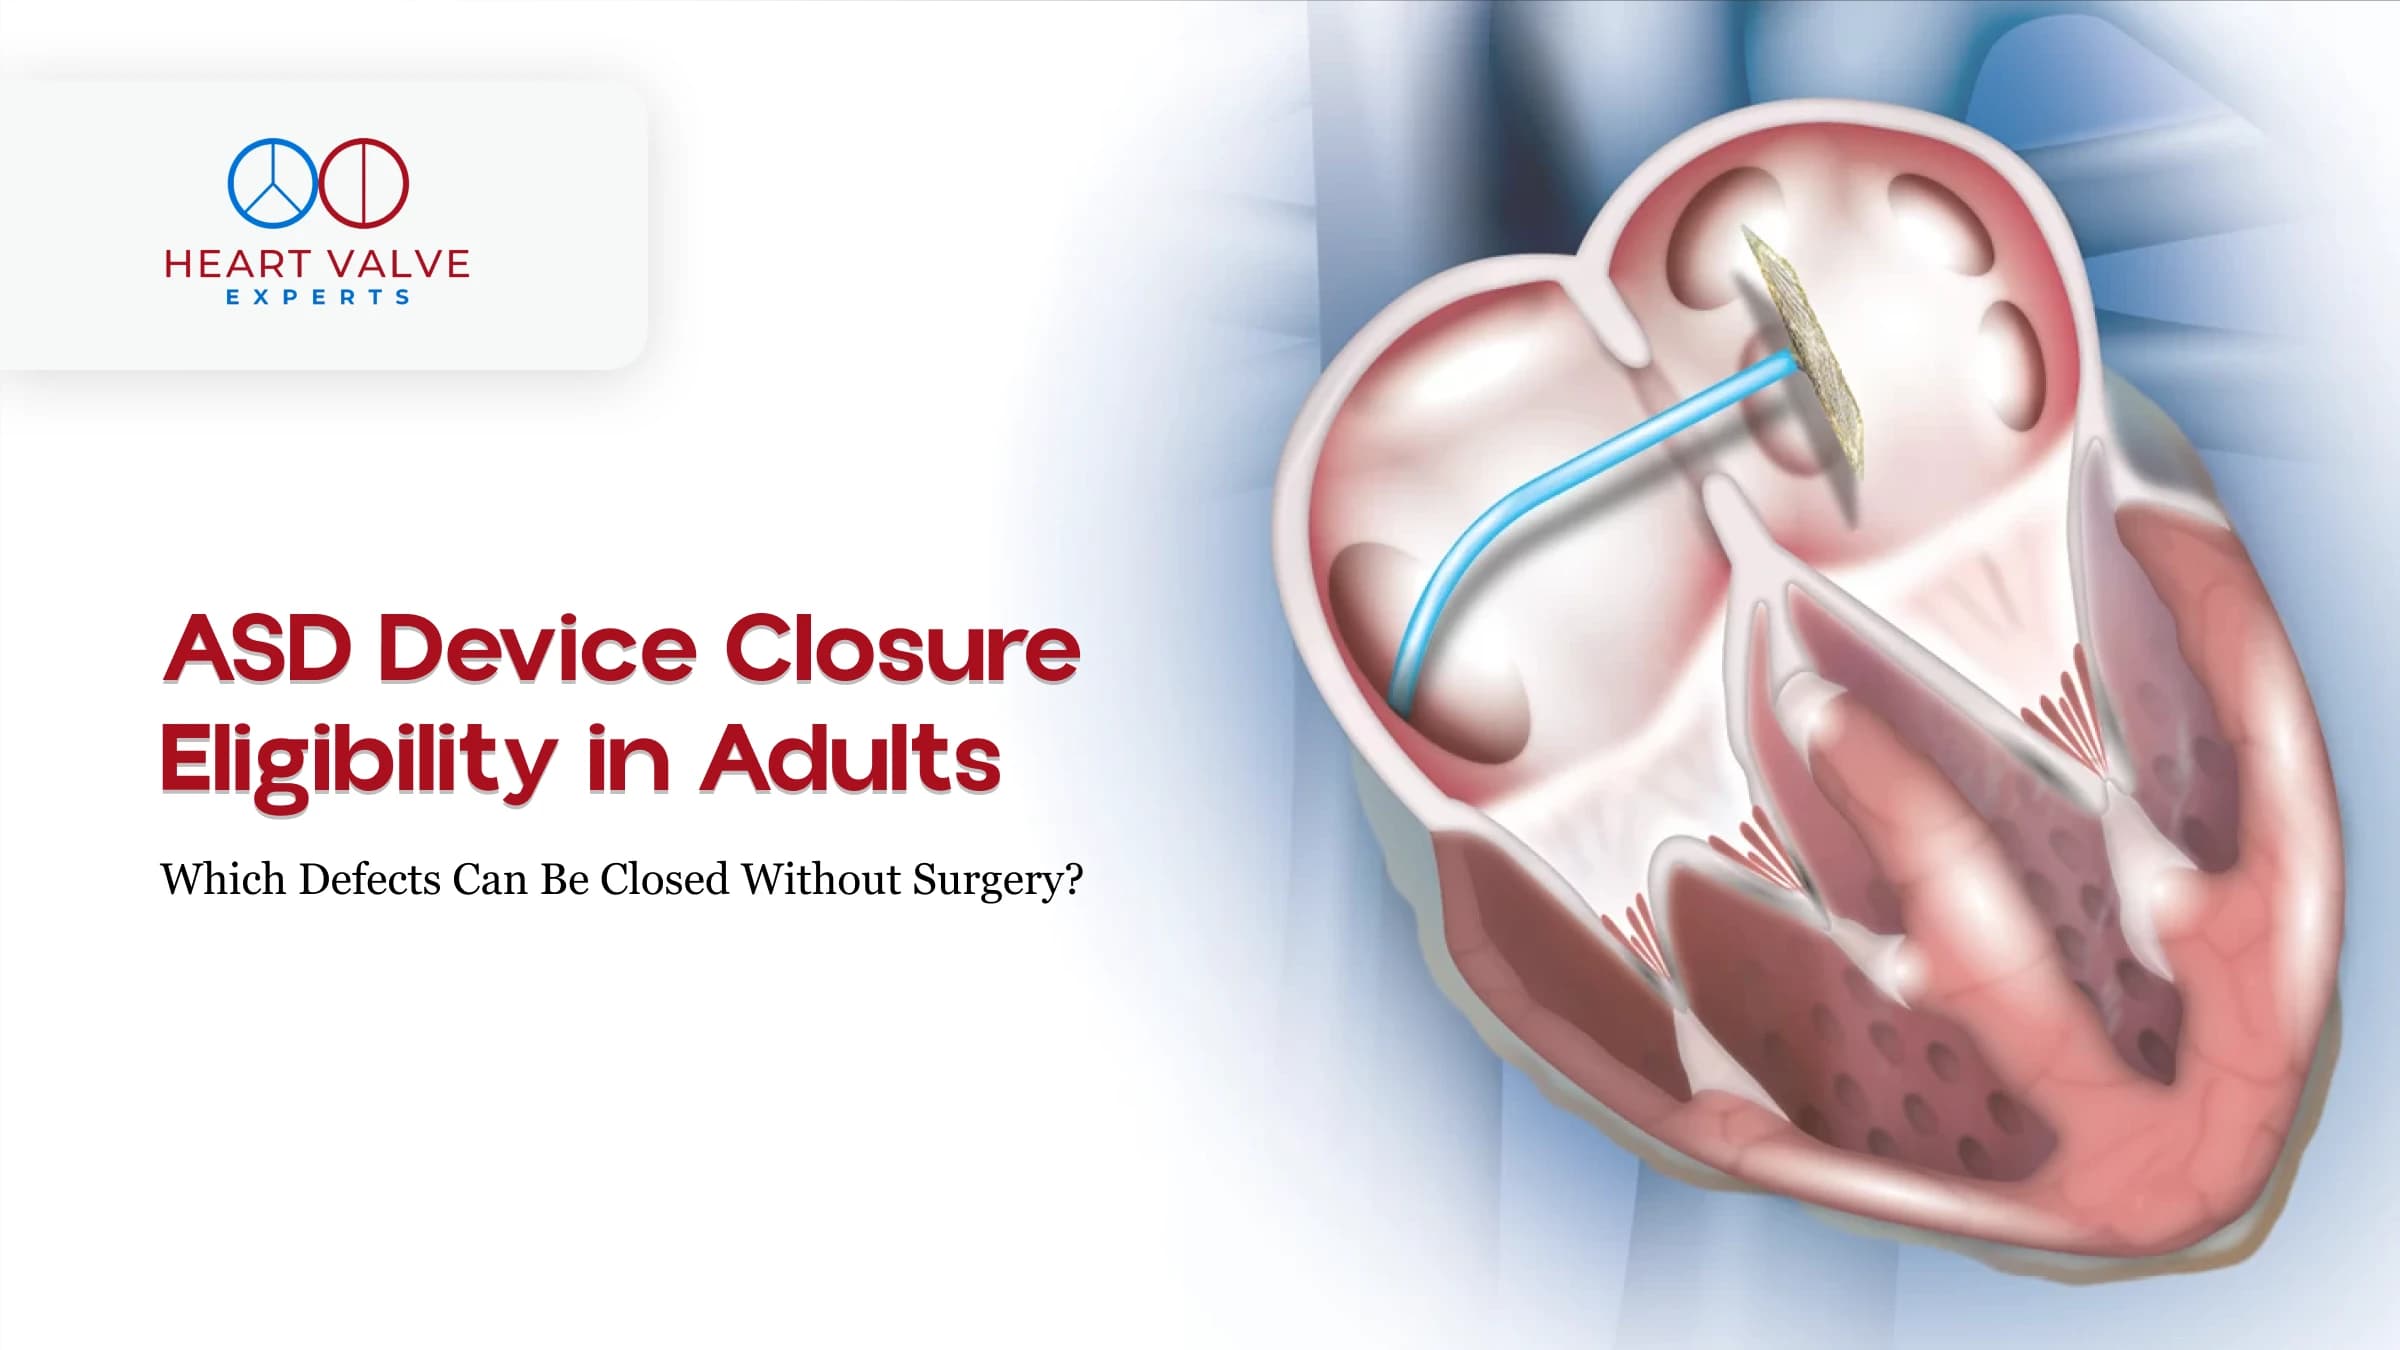
If an ASD needs to be closed, open-heart surgery may not be necessary. Some adults can have a minimally invasive procedure called transcatheter device closure. A cardiologist passes a thin tube called a catheter through a vein in the groin, the area where the upper thigh meets the lower abdomen, and guides the closure device to the opening in the heart.
If an ASD needs to be closed, open-heart surgery may not be necessary. Some adults are eligible for the ASD device closure procedure, a minimally invasive alternative also known as transcatheter device closure. During this atrial septal defect treatment, a cardiologist passes a thin tube called a catheter through a vein in the groin, the area where the upper thigh meets the lower abdomen, and guides the closure device to the opening in the heart.
Whether this is possible depends on three main questions:
The answer cannot be determined from the size of the hole alone.
| ASD finding | Is device closure possible? |
| Ostium secundum ASD with suitable surrounding tissue | Often yes |
| Large secundum ASD | Sometimes. Size alone does not decide eligibility. |
| Multiple or fenestrated secundum ASDs | Sometimes, depending on their location and surrounding tissue. |
| Secundum ASD with a deficient rim | Sometimes. The location and amount of missing supporting tissue matter. |
| Primum ASD | Usually requires surgery. |
| Superior sinus venosus ASD | Selected patients may be suitable for specialised covered-stent treatment. |
| Severe irreversible pulmonary vascular disease/Eisenmenger physiology | ASD closure should not be performed. |
| Significant left-heart filling-pressure problem | Requires specialist assessment before closure. |
This table is only a general guide. Imaging and, in some patients, heart catheterisation are needed to determine individual eligibility.
Atrial Septal Defect Treatment in Adults: Is It Always Needed?
Not always.
Atrial septal defect treatment in adults is not automatic just because a defect is found. A small ASD that is not causing important extra blood flow or enlargement of the right side of the heart may only need monitoring.
An ASD may need closure even if a person has few symptoms. Doctors look for signs that too much blood is passing from the left side of the heart to the right side and placing extra volume on the right ventricle.
One measurement doctors may use is Qp:Qs, which compares blood flow through the lungs with blood flow through the rest of the body. A Qp:Qs of 1.5 or higher is generally considered evidence of a haemodynamically significant shunt, particularly when there is enlargement of the right side of the heart.
The 2025 ACC/AHA adult congenital heart disease guideline recommends ASD closure when there is a significant left-to-right shunt, generally Qp:Qs ≥1.5, together with enlargement of the right ventricle, provided significant pulmonary arterial hypertension and significant left-heart disease are absent.
Symptoms such as breathlessness, tiredness or reduced ability to exercise can also be important, but symptoms alone do not decide whether an ASD should be closed.
Closure is also recommended in adults with an unrepaired ASD when there is evidence or strong suspicion of paradoxical embolism, a blood clot that crosses the ASD and enters the body’s arterial circulation.

Ostium Secundum ASD
An ostium secundum ASD is the type most commonly treated without surgery.
It is located in the central part of the wall between the atria. If there is enough suitable tissue around the opening, a closure device can often be placed securely.
When an isolated secundum ASD needs closure and its anatomy is suitable, the 2025 ACC/AHA guideline generally prefers transcatheter closure over surgery because it can reduce hospital stay and recovery time.
A primum ASD is located lower in the atrial septum and can occur with abnormalities of the heart valves.
A conventional ASD closure device cannot repair these associated structural problems. Therefore, primum ASDs usually require surgery when treatment is needed.
A sinus venosus ASD is often associated with pulmonary veins that connect abnormally to the heart.
These defects have traditionally been treated surgically. However, selected superior sinus venosus ASDs can now be treated using a specialised covered-stent technique when the anatomy is suitable.
This is different from standard secundum ASD device closure. Detailed imaging and an experienced adult congenital heart disease team are required.
Not by itself.
There is no single maximum ASD diameter that applies to every adult.
Doctors assess:
A 2025 study included adults with large, multiple and rim-deficient secundum ASDs who underwent transcatheter closure, showing that challenging anatomy can sometimes be treated successfully at experienced centres.
However, this does not establish a universal size limit. A smaller ASD may still be unsuitable if there is not enough tissue to hold a device safely.
The tissue surrounding an ASD is called the septal rim. It helps hold the closure device in position.
Having a deficient or small rim does not automatically mean device closure is impossible.
Doctors consider where the deficient rim is located, how much tissue is available, the size and shape of the ASD and the type of device being considered.
Some rim deficiencies can be managed successfully. Others may make the device unstable or bring it too close to important structures.
Before releasing a device, the cardiologist checks that it is stable and is not interfering with nearby veins, heart valves or the aortic root.
Sometimes.
Some adults have several small openings or a fenestrated ASD, meaning the septum contains multiple openings.
One device may sometimes cover several nearby openings. In other cases, more than one device may be considered.
If the openings are widely separated or the septum is very complex, surgery may provide a safer or more complete repair.
A standard transthoracic echocardiogram is usually the first test. It can show:
The 2025 ACC/AHA guideline recommends cardiac MRI, transoesophageal echocardiography or cardiac CT when detailed information about the defect, surrounding tissue and pulmonary veins is needed before repair.
Some patients need cardiac catheterisation, particularly when pulmonary hypertension is suspected.
This allows doctors to directly measure pressures inside the heart and lungs and calculate pulmonary vascular resistance.
Not Sure Whether Device Closure Is Suitable?
ASD size is only one part of the assessment. Detailed imaging and heart function also help determine whether device closure or surgery may be appropriate.
Button: Consult an ASD Specialist
Pulmonary vascular resistance (PVR) measures how difficult it is for blood to flow through the blood vessels in the lungs.
If PVR becomes very high, completely closing an ASD may be unsafe.
For adults with a significant shunt (Qp:Qs ≥1.5) and right-ventricular enlargement, the 2025 ACC/AHA guideline uses the following approach when significant left-heart disease is absent:
A 2023 observational study found that older age and higher PVR were associated with a greater chance of pulmonary hypertension persisting after ASD closure.
People with ASD and pulmonary arterial hypertension should therefore be evaluated by specialists experienced in both conditions.
Normally, an ASD allows extra blood to flow from the left side of the heart to the right side and then to the lungs. If this extra blood flow continues for many years, it can sometimes damage the small blood vessels in the lungs and cause the pressure in them to become very high. In severe cases, the pressure on the right side of the heart can rise so much that blood starts flowing through the ASD in the opposite direction, from the right side to the left side of the heart. This is called Eisenmenger physiology.
In Eisenmenger physiology, closing the ASD can be dangerous and is not recommended. These patients are usually managed by specialists in adult congenital heart disease and pulmonary hypertension.
Why Does Left-Heart Function Matter?
In some adults, the main pumping chamber of the heart, called the left ventricle, becomes stiff and does not relax normally. This can cause pressure to build up on the left side of the heart. An ASD may provide a pathway that helps relieve some of this pressure. If the ASD is closed, that pressure can rise and may worsen symptoms in some patients. For this reason, doctors assess how well the left side of the heart is working before deciding whether ASD closure is safe. Some patients may need additional tests, including cardiac catheterisation, before a treatment decision is made.
Surgery may be recommended when:
Needing surgery does not necessarily mean the heart condition is more severe. It may simply mean that surgery provides a safer and more complete repair for that particular anatomy.
For suitable patients, transcatheter ASD closure avoids opening the chest and usually allows a shorter hospital stay and recovery than conventional open-heart surgery. A 2026 systematic review of observational studies found high procedural success with both transcatheter and surgical closure. In adults, reported success was about 97% with transcatheter treatment and 98% with surgery, while transcatheter closure was associated with shorter hospital stays and fewer major complications.
Most procedures are completed without serious problems, but complications can occur. These may include bruising where the catheter is inserted, abnormal heart rhythms and a small residual leak around the device. Less common but more serious complications include movement of the device, a blood clot forming on the device, significant arrhythmias, erosion or perforation of nearby heart tissue, fluid around the heart and stroke. In a Finnish nationwide study of 1,000 patients, device embolisation occurred in 1.0% and erosion in 0.4%.
Ask a cardiologist experienced in adult congenital heart disease whether your ASD needs treatment and whether device closure is possible.
If available, take these records to your appointment:
Useful questions to ask include:
Discuss Your ASD Treatment Options With a Specialist
A specialist assessment can help clarify whether your ASD needs treatment and which approach may be suitable for your individual heart anatomy and circulation.
Button: Schedule a Consultation
Whether an ASD can be closed without surgery depends on much more than the size of the opening.
For many adults with a haemodynamically significant secundum ASD and suitable anatomy, transcatheter device closure is usually preferred to surgery.
Primum ASDs, complex anatomy, inadequate supporting tissue, some pulmonary venous abnormalities and associated heart problems may require surgery. Selected superior sinus venosus ASDs may be suitable for specialised covered-stent treatment.
Pulmonary hypertension and left-heart filling pressure must also be considered because closing an ASD that the circulation cannot safely tolerate may cause harm.
The safest decision comes from combining the type of ASD, detailed imaging, its effect on the heart and lungs, and the patient’s overall heart function rather than relying on defect size alone.
This article provides general patient education. It does not determine whether an individual patient should undergo ASD closure. Treatment decisions should be made after assessment by a cardiologist experienced in adult congenital heart disease.
No. Transcatheter device closure is most commonly used for secundum ASDs with suitable anatomy. Primum ASDs usually require surgery, while selected superior sinus venosus ASDs may be suitable for specialised covered-stent treatment. The type of ASD, surrounding tissue, pulmonary veins and other heart abnormalities all affect eligibility.
Sometimes. There is no single ASD size that determines whether device closure is possible. Doctors also assess the shape of the opening, the amount and location of surrounding tissue, nearby heart structures and whether a device can be positioned securely.
No. Some small ASDs that do not cause significant abnormal blood flow or enlargement of the right side of the heart may only need monitoring. The decision to close an ASD depends on its effects on the heart and circulation, not simply on whether an opening is present.
A transthoracic echocardiogram is usually part of the initial assessment. Depending on the ASD and the information needed, doctors may also use transoesophageal echocardiography, cardiac MRI or cardiac CT. Cardiac catheterisation may be needed in some patients, particularly when pulmonary hypertension is suspected.
Sometimes. Eligibility depends partly on pulmonary vascular resistance (PVR) and other haemodynamic findings. Some people with pulmonary hypertension may still be suitable for closure, while advanced pulmonary vascular disease can make closure unsafe. In Eisenmenger physiology, ASD closure is not recommended.
Both transcatheter and surgical ASD closure have high reported success rates in appropriately selected patients. Device closure avoids opening the chest and is generally associated with a shorter hospital stay and recovery. However, surgery may be safer or more appropriate when the anatomy is unsuitable for a device or other heart abnormalities also need repair.
Doctors consider the type and size of the ASD, the surrounding septal tissue, the number and position of openings, pulmonary vein anatomy, pulmonary pressures, heart function and any other cardiac abnormalities. These factors are assessed together rather than using ASD size alone.
A small ASD does not automatically need closure. If it is not causing significant abnormal blood flow or enlargement of the right side of the heart, monitoring may be more appropriate. If closure is indicated, anatomy and surrounding tissue are considered when deciding whether a device can be used.
Sometimes. One device may cover several nearby openings, while some patients may require more than one device. Widely separated openings or complex septal anatomy may make surgery a more suitable option.
If device closure is unsuitable, surgery may be considered when the ASD still needs treatment. This does not necessarily mean the condition is more severe; surgery may simply provide a safer or more complete repair for that particular anatomy.

About The Author
With over 15 years of expertise, Dr. Phatarpekar is recognised as a renowned interventional cardiologist in Mumbai, specialising in complex coronary interventions, structural heart procedures, and pioneering work in Transcatheter Aortic Valve Implantation (TAVI).
● Blogs